Testosterone + Trenbolone + Masteron (TTM)
Risk: HighReview the physique claims and health risks of combining testosterone, trenbolone and drostanolone.
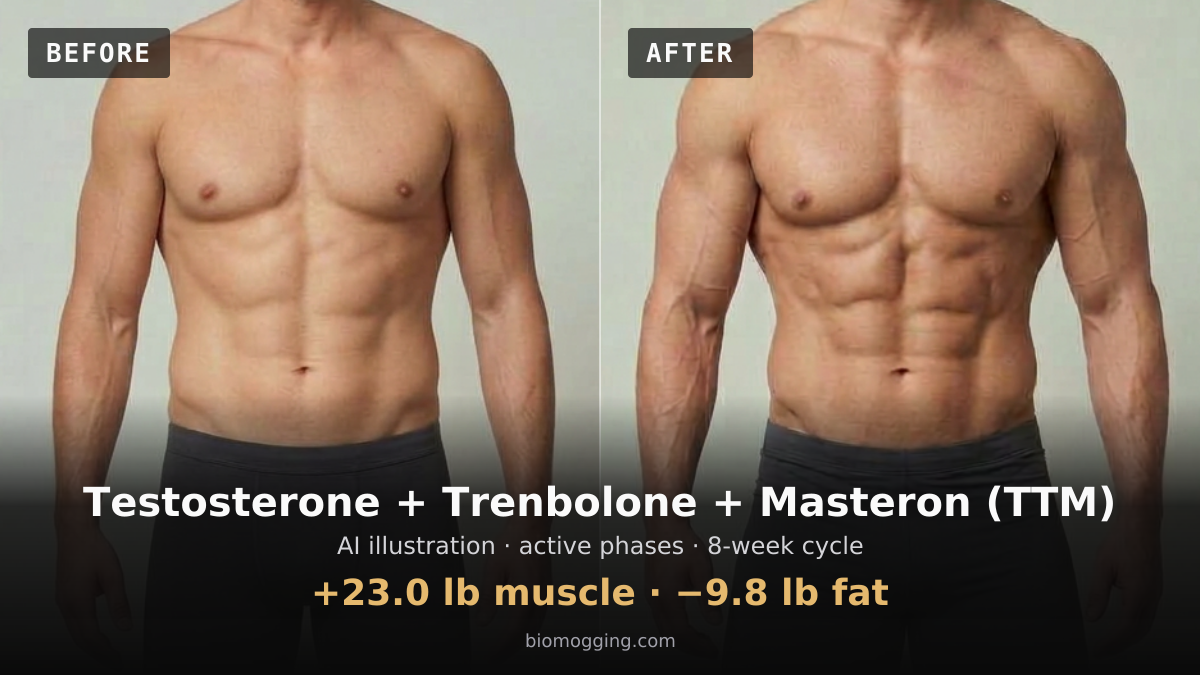
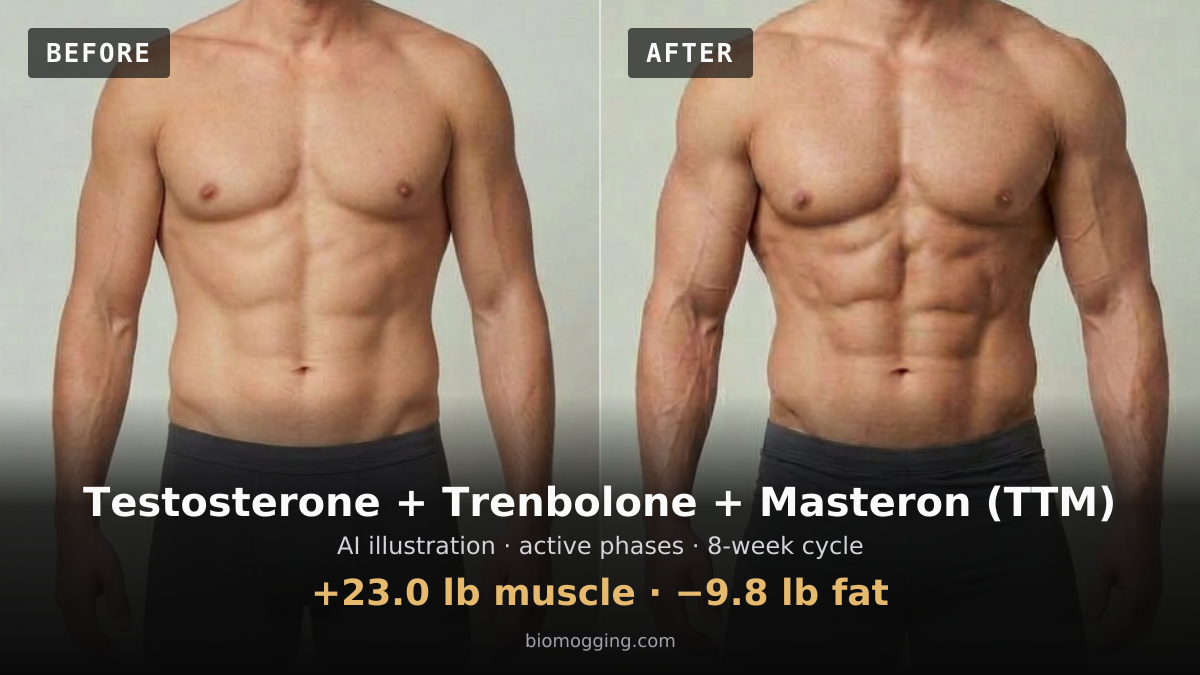
Composition: 3 Steroids
Overview
The cited studies examined men using varied androgens and did not test this three-drug schedule, its ratios, or its post-cycle therapy.
This profile is written for intermediate adult male users with prior anabolic-androgenic steroid (AAS) experience who are comparing testosterone, trenbolone, and drostanolone (Masteron) to evaluate the reported physique claims and health risks of combining them. Prior experience with testosterone or simpler regimens does not establish physiological tolerance to this three-compound stack, justify dose escalation, or define a safe minimum total dose.
No clinical trial, regulatory approval, or medical guideline establishes a validated dose, compound ratio, or phase length for combining testosterone, trenbolone, and drostanolone. What circulates in bodybuilding practice is anecdotal convention rather than a tested clinical protocol. Evaluating this stack therefore requires separating what is known about each individual agent from what remains unknown when they are combined:
- Testosterone is an endogenous human hormone with established clinical pharmacology. It undergoes conversion via 5-alpha-reductase to dihydrotestosterone (DHT) and via aromatase to estradiol, supporting androgenic signaling alongside estrogen-dependent vascular, neural, skeletal, and lipid functions.
- Drostanolone (Masteron) is a synthetic 2-alpha-methylated DHT derivative historically used in limited palliative oncology settings for female breast cancer. Because it is already 5-alpha-reduced, it cannot aromatize into estradiol. However, a common misconception in non-medical practice is that drostanolone acts as a reliable aromatase inhibitor (AI) capable of controlling estradiol derived from co-administered testosterone. Data on drostanolone as an individual compound do not establish dependable systemic estrogen suppression in men taking supraphysiological testosterone.
- Trenbolone is a veterinary 19-norandrogen developed to increase feed efficiency and muscle mass in livestock. It has never been approved for human therapeutic use, creating distinct uncertainties regarding its long-term human neurotoxicity, cerebrovascular effects, myocardial remodeling, and renal toxicity that cannot be inferred from clinical testosterone studies.
Similarly, combination-specific clinical data for this exact trio do not exist. Broader findings on multi-androgen health risks and endocrine recovery come largely from observational studies of self-selected AAS users—such as the HAARLEM observational cohort report and related PubMed-indexed androgen research—which tracked heterogeneous, mixed androgen exposures rather than testing a standardized testosterone-trenbolone-drostanolone protocol.
Why this stack works
Pairwise and Cumulative Interactions#
Assessing testosterone, trenbolone, and drostanolone together highlights overlapping androgenic pathways, competing binding dynamics, and cumulative organ toxicities that cannot be solved simply by adjusting compound ratios:
- Aromatization, SHBG Binding, and the Drostanolone Estrogen Fallacy: Testosterone is the only aromatizing hormone in this stack and serves as the necessary substrate for physiological estradiol maintenance. Drostanolone binds strongly to sex hormone-binding globulin (SHBG) and suppresses hepatic SHBG synthesis. By displacing testosterone from SHBG, drostanolone can increase the unbound fraction of circulating testosterone available for both androgen receptor binding and peripheral aromatization. Although drostanolone exhibited anti-estrogenic activity in historical breast tissue models, it does not reliably inhibit the aromatase enzyme in men. Relying on drostanolone to control estradiol can leave excess aromatization from high testosterone unaddressed; conversely, combining moderate testosterone, drostanolone, and routine prophylactic aromatase inhibitors can excessively suppress estradiol, worsening atherogenic lipid shifts, joint pain, and endothelial dysfunction.
- Progestogenic Signaling, Prolactin, and Laboratory Assay Interference: Trenbolone binds with high affinity to both androgen and progesterone receptors. Progestogenic stimulation, particularly in the presence of elevated estradiol, can sensitize pituitary lactotrophs and raise serum prolactin, contributing to lactation-related gynecomastia and sexual dysfunction. In addition, circulating trenbolone metabolites cross-react with standard estradiol immunoassays (ECLIA/chemiluminescence), frequently producing falsely elevated estradiol results. Treating an artifactual lab value with an aromatase inhibitor can crash actual systemic estradiol. Consequently, monitoring during trenbolone exposure requires high-sensitivity liquid chromatography–tandem mass spectrometry (LC-MS/MS) estradiol testing, and both aromatase inhibitors and dopamine agonists must remain strictly conditional on verified laboratory abnormalities and clinical symptoms.
- Additive Cardiometabolic, Hematologic, and Neuropsychiatric Load: All three androgens suppress high-density lipoprotein (HDL) cholesterol and increase low-density lipoprotein (LDL) cholesterol; non-aromatizing DHT derivatives and 19-norandrogens markedly stimulate hepatic lipase, accelerating unfavorable lipid remodeling. Concurrent administration also drives erythropoiesis (raising hematocrit and blood viscosity), increases sympathetic nervous system tone, and elevates blood pressure. Trenbolone adds poorly characterized human risks of severe insomnia, night sweats, mood destabilization, and elevated renal filtration markers.
Endocrine Suppression, Fertility, and Evidence Limits for Transition and PCT#
Combining an aromatizing androgen, a DHT derivative, and a progestogenic 19-norandrogen causes rapid, profound suppression of hypothalamic gonadotropin-releasing hormone (GnRH) and pituitary luteinizing hormone (LH) and follicle-stimulating hormone (FSH). This halts endogenous intratesticular testosterone production and severely impairs spermatogenesis, leading to oligozoospermia or azoospermia.
Observational literature—including the HAARLEM study in Human Reproduction and associated PubMed-indexed follow-up analyses—provides important context on recovery after mixed androgen use, but its boundaries must be clearly understood:
- Observation Checkpoints vs. Exposure or Guaranteed Recovery: The HAARLEM cohort evaluated men using mixed, self-administered androgen regimens rather than this specific three-drug combination. In that research, three months after androgen cessation and one year after study enrollment were investigator observation times used to measure endocrine and semen parameters. Neither checkpoint represents a recommended time on these drugs, a guaranteed timeline for full hormonal or fertility recovery, or a clinical mandate.
- Ester Selection and Post-Cycle Therapy (PCT) Uncertainty: Because no clinical source establishes a safe dose, ratio, or duration for this stack, the reference schedule pairs short esters (Testosterone Propionate, Trenbolone Acetate, and Drostanolone Propionate) administered three times weekly. Matching short esters prevents prolonged residual suppression from slow-clearing 19-norandrogen depots after stopping and allows rapid discontinuation if intolerable neuropsychiatric or cardiovascular toxicity develops. Following a 1-week ester clearance transition, a selective estrogen receptor modulator (SERM) phase is included to reflect standard reported practice aimed at encouraging gonadotropin resumption. However, controlled clinical evidence proving that PCT reliably accelerates or guarantees complete hypothalamic-pituitary-gonadal (HPG) axis or spermatogenic recovery after multi-agent 19-norandrogen exposure is limited.
Protocol timeline
3 phases · 13 weeks total
Timeline shows the 13-week cycle. Bars overlap when phases run concurrently. Click a bar to jump to its detail card.
The interactive timeline loads here. Phase details are available below.
Core Androgen Schedule (Weeks 1–8)#
- Testosterone Propionate: 75 mg via deep intramuscular injection 3 times weekly (Monday, Wednesday, Friday) = 225 mg/week per-compound total.
- Trenbolone Acetate: 50 mg via deep intramuscular injection 3 times weekly (Monday, Wednesday, Friday) = 150 mg/week per-compound total.
- Drostanolone Propionate (Masteron Propionate): 75 mg via deep intramuscular injection 3 times weekly (Monday, Wednesday, Friday) = 225 mg/week per-compound total.
- Combined Weekly Steroid Mass: 600 mg/week (sum of Testosterone Propionate 225 mg/week + Trenbolone Acetate 150 mg/week + Drostanolone Propionate 225 mg/week; ancillary medications excluded). This mass sum is a bookkeeping total, not a potency-equivalent measure or safety threshold.
Routine Support & Monitoring#
- Blood Pressure & Vital Checks: Measure seated blood pressure at least 3 times weekly; monitor resting heart rate and sleep duration daily.
- Laboratory Panel (Baseline and Week 4): Complete blood count (hematocrit/hemoglobin), comprehensive metabolic panel, cystatin C, fasting lipid profile, serum prolactin, and sensitive estradiol via LC-MS/MS (standard immunoassay estradiol tests cross-react with trenbolone metabolites and must not be used to guide dosing).
Conditional Interventions (Only If Confirmed by Symptoms and Labs)#
- Anastrozole (unlinked ancillary aromatase inhibitor; conditional only upon clinical hyperestrogenic symptoms paired with elevated estradiol confirmed via LC-MS/MS): 0.25 mg orally twice weekly (Monday, Thursday) = 0.5 mg/week per-compound total. Do not administer routinely or assume drostanolone controls estradiol.
- Cabergoline (unlinked ancillary dopamine agonist; conditional only upon clinical symptoms paired with laboratory-confirmed elevated serum prolactin): 0.25 mg orally once weekly (Monday) = 0.25 mg/week per-compound total. Do not use prophylactically.
This proposed schedule uses short propionate and acetate esters to synchronize clearance and permit rapid cessation if severe sleep disruption, neuropsychiatric shifts, hypertension, or cardiopulmonary strain develop. No clinical source establishes a validated dose, ratio, or duration for this trio. In reported practice, some users split short esters into daily administrations to reduce peak-to-trough fluctuations, whereas substituting enanthate esters extends both active exposure and required pre-PCT clearance time.
Washout & Clearance Protocol (Week 9)#
- Exogenous Androgens: 0 mg/week (all administrations of Testosterone Propionate, Trenbolone Acetate, and Drostanolone Propionate cease after the final Friday injection of Week 8).
- Clearance Interval: Week 9 is the full calendar week with no scheduled androgens between the last Friday in Week 8 and the proposed PCT phase in Week 10. Individual clearance cannot be determined from calendar dates alone.
- Conditional Ancillaries: Discontinue any conditional on-cycle aromatase inhibitor or dopamine agonist unless continuing under direct physician supervision for a documented laboratory abnormality.
- Monitoring: Track blood pressure, mood, energy, and sleep normalization as supraphysiological androgen levels clear.
A 1-week transition window aligns with the short terminal half-lives of propionate and acetate esters. If long esters (such as Testosterone Enanthate, Trenbolone Enanthate, or Drostanolone Enanthate) are used instead, the clearance gap prior to PCT must be extended (typically 2 to 3 weeks) so lingering exogenous androgens do not blunt pituitary responsiveness during PCT.
Primary SERM Schedule (Weeks 10–13)#
- Tamoxifen Citrate (unlinked ancillary SERM): 20 mg orally once daily (every morning) = 140 mg/week per-compound total.
Follow-up after the timeline (approximately Weeks 17–19).
- Post-PCT Blood Work: Repeat comprehensive labs 4 to 6 weeks after completing Tamoxifen (total and free testosterone, LH, FSH, sensitive estradiol via LC-MS/MS, prolactin, CBC/hematocrit, CMP, cystatin C, and fasting lipids) to assess whether endogenous hypothalamic-pituitary-gonadal (HPG) signaling has resumed.
- Fertility Evaluation: If reproductive capacity is a priority, perform a clinical semen analysis during post-cycle follow-up, recognizing that spermatogenic recovery often lags behind serum gonadotropin normalization.
Tamoxifen citrate is presented as one definite reference schedule; alternative reported protocols use Clomiphene citrate (e.g., 25 mg orally once daily, equal to 175 mg/week) or incorporate human chorionic gonadotropin (hCG) during the late cycle/clearance transition to stimulate testicular steroidogenesis prior to SERM initiation. Users returning to clinician-managed testosterone replacement therapy (TRT) transition directly to maintenance testosterone rather than performing PCT. Controlled evidence for PCT after 19-norandrogen exposure is limited, and PCT does not guarantee full or rapid recovery.
Compounds in this stack
3 linked · tap for full guide
How they work together
Multipliers applied to the projection above when these compounds run together. Values > 1 indicate a bonus, < 1 a penalty.
| Pair | Type | Lean | Fat loss | Recovery |
|---|---|---|---|---|
| synergistic | ×1.15 | ×1.10 | ×1.08 | |
| synergistic | ×1.10 | ×1.15 | ×1.07 |
Cycle outcome projection
Projection across all phases (13 weeks total) using the same math as the stack-calculator tool. Adjust gender, cycle length, and goal to see how the numbers move.
Body Transformation Preview


Lean Mass Gain
25.3 lbs
18.9–31.6 lbs range
Fat Loss
10.8 lbs
8.1–13.4 lbs range
Lean Synergy Bonus
+26%
from compound pairing
Fat Loss Synergy
+26%
from compound pairing
Per-Compound Contribution
Lean Gain by Week
Conclusion
Comparing testosterone, trenbolone, and drostanolone underscores the gap between recreational physique claims and clinical evidence. While individual compound pharmacology explains why testosterone supplies necessary estrogenic substrate, why drostanolone alters SHBG binding without serving as a dependable aromatase inhibitor, and why trenbolone introduces potent androgenic and progestogenic activity alongside unquantified human toxicities, no clinical study establishes a safe or effective protocol for combining them. Observational cohorts such as the HAARLEM study and related PubMed-indexed research demonstrate that mixed supraphysiological androgen exposures profoundly suppress endocrine and reproductive function, with study assessments at three months post-cessation and one year post-enrollment serving as research observation checkpoints rather than guaranteed recovery schedules. Anyone reviewing reference protocols for this stack should prioritize rigorous cardiovascular, renal, hematologic, and LC-MS/MS endocrine monitoring.
This combination carries high systemic risk and should be avoided by:
- First-time or novice AAS users, as concurrent exposure to three compounds—including a veterinary 19-norandrogen—prevents clear identification of which drug is driving adverse effects.
- Women, due to the high likelihood of rapid, irreversible virilization from potent androgenic signaling.
- Individuals with cardiovascular, cerebrovascular, or hematologic conditions, including hypertension, dyslipidemia, arrhythmias, left ventricular hypertrophy, coronary artery disease, elevated baseline hematocrit/polycythemia, or a history of thrombosis.
- Individuals with renal or hepatic impairment, as trenbolone and combined high-dose androgens increase cardiometabolic and renal strain.
- Individuals with psychiatric or sleep disorders, including severe anxiety, depression, bipolar disorder, impulse-control conditions, or chronic insomnia, which can be sharply exacerbated by trenbolone.
- Men with known or suspected prostate or breast carcinoma, in whom androgens are strictly contraindicated.
- Men seeking near-term fertility or unwilling to accept prolonged hypogonadism, as deep gonadotropin and spermatogenic suppression after 19-norandrogen exposure may take many months to resolve and recovery is not guaranteed by post-cycle therapy.
Updated 2026-11-18