Testosterone + Primobolan + Anavar
Risk: HighReview the claimed physique effects and overlapping risks of testosterone, methenolone and oxandrolone.
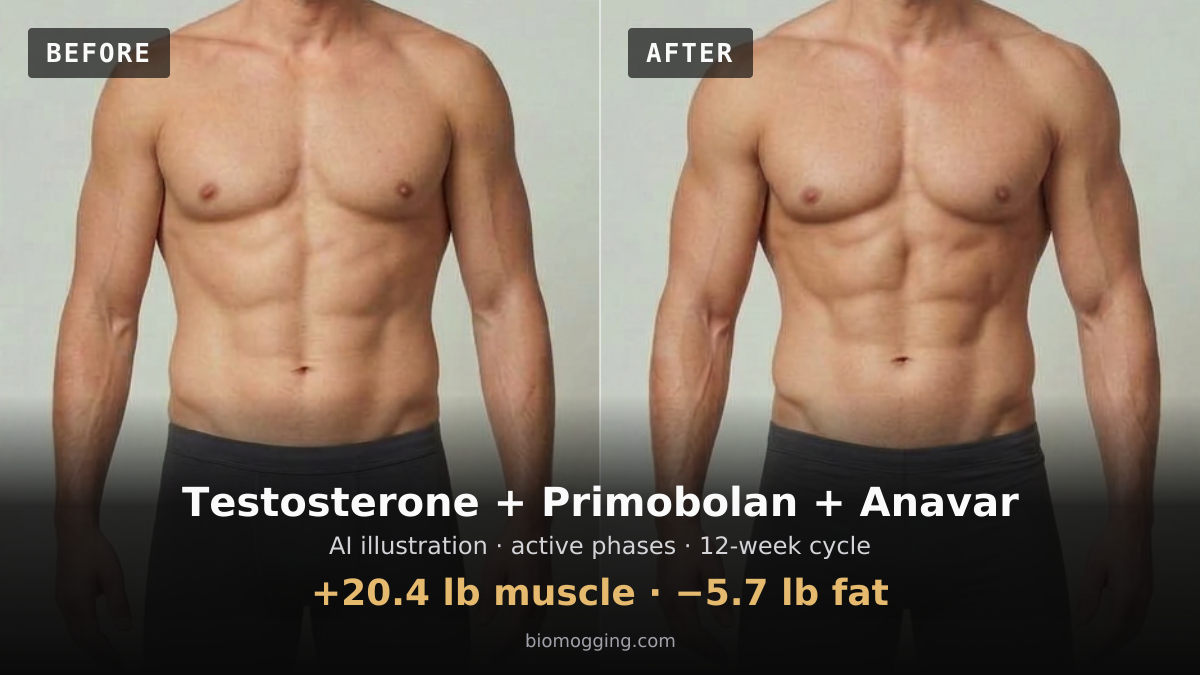
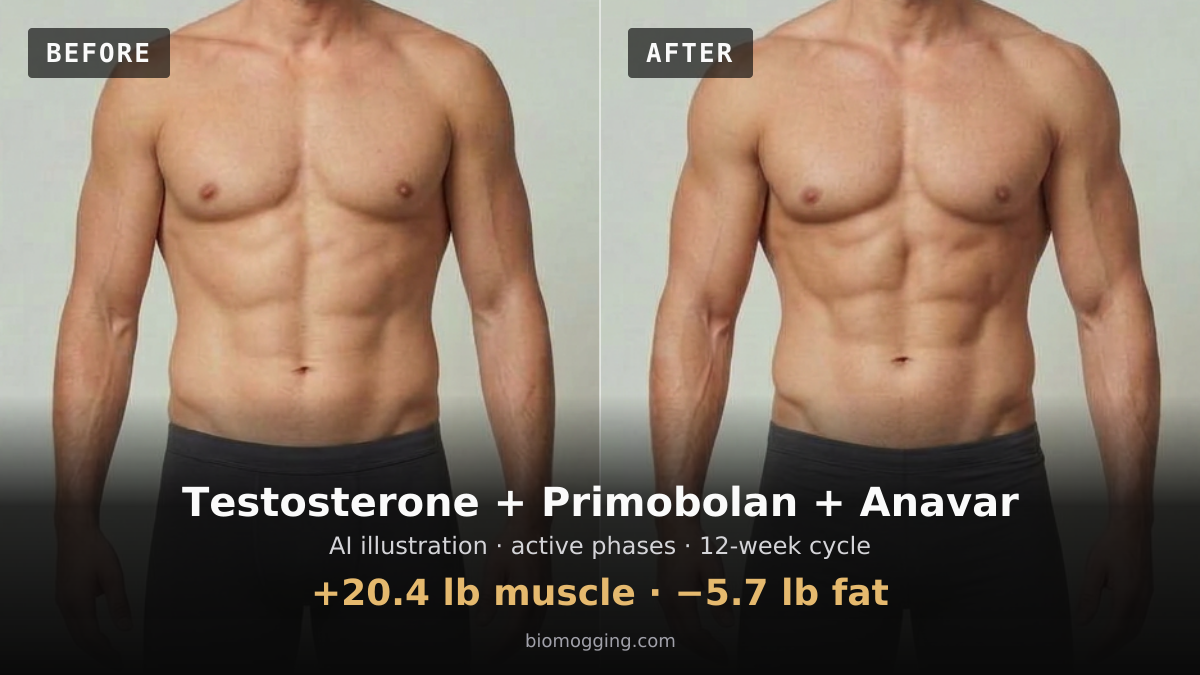
Composition: 3 Steroids
Overview
The cited studies examined men using varied androgens and did not test this three-drug schedule, its ratios, or its post-cycle therapy.
This review is written for intermediate adult male users with prior anabolic-androgenic steroid (AAS) experience who are comparing injectable testosterone, methenolone (Primobolan), and oral oxandrolone (Anavar). No clinical study establishes a validated dose, ratio, or phase duration for combining these three compounds. While pharmaceutical data describe each agent individually, stacking an aromatizable androgen with two non-aromatizable dihydrotestosterone (DHT) derivatives produces overlapping endocrine, lipid, and hepatic risks that cannot be safely extrapolated from single-compound studies. Prior experience does not establish tolerance or justify dose escalation.
Why this stack works
Endocrine Suppression and Estradiol Uncertainty All three compounds suppress hypothalamic-pituitary-gonadal (HPG) axis signaling and impair spermatogenesis. Because neither methenolone nor oxandrolone aromatizes into estradiol, testosterone provides the sole substrate for physiological estrogen maintenance. In reported practice, methenolone is hypothesized to reduce aromatase activity or estrogenic signaling, prompting users to experiment with specific testosterone-to-methenolone ratios. However, no clinical evidence establishes a universal safe ratio. Excessive methenolone relative to testosterone—or routine aromatase inhibitor (AI) use—risks estradiol deficiency (adversely affecting lipids, joints, and sexual function), whereas high testosterone doses can still cause hyperestrogenism. An AI should therefore remain strictly conditional on both symptoms and bloodwork, never routine. SHBG, Lipid, and Hepatic Interactions Both methenolone and oral oxandrolone markedly suppress sex hormone-binding globulin (SHBG), increasing free androgen fractions and altering clearance relative to monotherapy. Per the archived oxandrolone label, C17-alpha-alkylated oxandrolone poses severe risks to lipid profiles (profound HDL reduction and LDL elevation) and hepatic health (elevated transaminases, cholestatic hepatitis, and peliosis hepatis). Adding oxandrolone only during the second half of the schedule limits cumulative hepatotoxic and atherogenic exposure compared with full-cycle oral use. Recovery, Fertility, and Limits of PCT Evidence Observational data from the HAARLEM cohort study examined men using mixed androgen regimens (not this specific trio), using three months after cessation and one year after enrollment strictly as study observation checkpoints rather than prescribed exposure lengths or guaranteed recovery windows. After accounting for enanthate ester clearance, selective estrogen receptor modulator (SERM) post-cycle therapy (PCT) is commonly employed, though endocrine recovery literature demonstrates limited clinical evidence that PCT reliably accelerates or guarantees normalization of endogenous testosterone or fertility.
Protocol timeline
4 phases · 18 weeks total
Timeline shows the 18-week cycle. Bars overlap when phases run concurrently. Click a bar to jump to its detail card.
The interactive timeline loads here. Phase details are available below.
- Testosterone enanthate: 150 mg intramuscularly twice weekly (300 mg/week per-compound total).
- Methenolone enanthate (Primobolan): 100 mg intramuscularly twice weekly (200 mg/week per-compound total).
- Injectable base subtotal: 500 mg/week (sum of testosterone enanthate and methenolone enanthate; mass bookkeeping only, not a potency equivalent or safety threshold).
- Conditional intervention described for Weeks 1–6: Anastrozole (unlinked ancillary) 0.25 mg orally twice weekly only if symptoms and sensitive estradiol bloodwork confirm hyperestrogenism; do not use routinely given the risk of excessive estradiol suppression.
No clinical source establishes this dose or ratio; figures reflect a proposed reference schedule from reported practice. Obtain baseline and Week 6 bloodwork (lipids, hepatic panel, hematocrit, sensitive estradiol) before introducing oral oxandrolone.
The injectable base continues through Week 12. This phase adds Anavar during Weeks 7–12.
- Oxandrolone (Anavar): 10 mg orally twice daily (20 mg/day; 140 mg/week per-compound total).
- Total across both phases during Weeks 7–12: 640 mg/week (sum of testosterone enanthate, methenolone enanthate, and oral oxandrolone; mass bookkeeping only, not a potency equivalent or safety threshold).
Restricting C17-alpha-alkylated oxandrolone to Weeks 7–12 limits cumulative hepatic and HDL-suppressing exposure. Withhold or discontinue oxandrolone if mid-cycle labs reveal marked dyslipidemia or elevated liver transaminases.
- Discontinue testosterone enanthate, methenolone enanthate, and oral oxandrolone at the end of Week 12. - Administer no exogenous androgens or SERMs during Weeks 13–14 to allow intramuscular enanthate esters to decline before starting post-cycle therapy.
This clearance interval accounts for the slow release of enanthate esters. If transitioning directly to clinician-managed testosterone replacement therapy (TRT), neither this washout nor PCT applies.
- Tamoxifen citrate (unlinked ancillary): 20 mg orally once daily (140 mg/week per-compound total).
Follow-up after the timeline (approximately Weeks 22–24).
Repeat comprehensive bloodwork (LH, FSH, total and free testosterone, estradiol, lipid panel, liver enzymes) 4 to 6 weeks after completing PCT to evaluate endogenous HPG axis recovery.
SERM therapy is a reported practice to support gonadotropin rebound after androgen clearance, but clinical evidence does not prove it guarantees or accelerates full endocrine or fertility restoration.
Compounds in this stack
3 linked · tap for full guide
How they work together
Multipliers applied to the projection above when these compounds run together. Values > 1 indicate a bonus, < 1 a penalty.
| Pair | Type | Lean | Fat loss | Recovery |
|---|---|---|---|---|
| synergistic | ×1.15 | ×1.08 | ×1.10 |
Cycle outcome projection
Projection across all phases (18 weeks total) using the same math as the stack-calculator tool. Adjust gender, cycle length, and goal to see how the numbers move.
Body Transformation Preview


Lean Mass Gain
26.4 lbs
19.8–33.0 lbs range
Fat Loss
7.7 lbs
5.8–9.7 lbs range
Lean Synergy Bonus
+15%
from compound pairing
Fat Loss Synergy
+8%
from compound pairing
Per-Compound Contribution
Lean Gain by Week
Conclusion
Combining testosterone, methenolone, and oxandrolone pairs an aromatizable androgen base with two non-aromatizable DHT derivatives, compounding HPG axis suppression, SHBG reduction, and atherogenic lipid shifts beyond single-drug profiles. Because no clinical study validates doses, ratios, or durations for this trio, users face unpredictable estradiol balance alongside oral oxandrolone hepatotoxicity. Even with an ester washout and SERM PCT, complete endocrine and reproductive recovery is not guaranteed.
This combination should be avoided by women due to high risk of irreversible virilization, men seeking to preserve fertility during or shortly after use, and individuals with known or suspected carcinoma of the prostate or male breast. According to the archived oxandrolone label, additional contraindications and high-risk states include nephrosis, hypercalcemia, hepatic dysfunction, and baseline dyslipidemia or cardiovascular disease. Novice users without prior single-compound AAS experience should also avoid multi-agent stacks.
Updated 2026-11-18